


Is My Son a Late Bloomer—or Is Puberty Delayed?
Delayed puberty in boys is defined as no testicular enlargement by age 14. Many boys with delayed puberty are healthy late bloomers whose development will eventually progress on its own. But “he's probably just a late bloomer” is not the same thing as knowing that he is one.
That distinction matters.
Constitutional delay of growth and puberty is the most common cause of delayed puberty in boys, accounting for roughly 60–80% of cases in published series. Other boys may have nutritional or chronic health issues, pituitary or hypothalamic conditions, genetic differences, or problems affecting the testicles themselves.
Waiting can be appropriate once you understand what you're waiting on. Waiting without understanding the pattern can cost valuable time.
LIFE Pediatric Endocrinology is a national pediatric endocrinology practice caring for children and adolescents with growth, puberty and hormonal concerns. We evaluate puberty together with growth history, family development, bone age and, when appropriate, targeted laboratory testing to understand whether a boy is simply developing later—or whether there is another reason puberty has not progressed.
What Is Delayed Puberty in Boys?
Doctors define delayed puberty in boys as the absence of testicular enlargement by age 14.
Clinically, that generally means the testicles remain in the prepubertal range—less than approximately 4 mL in volume—and the boy remains at Tanner genital stage 1.
Age 14 is not an arbitrary cutoff. It represents approximately two standard deviations beyond the average age at which male puberty begins.
Importantly, delayed puberty describes timing. It does not tell us why puberty is delayed.
That is the question an evaluation is designed to answer.
What Is the First Sign of Puberty in a Boy?
The first true sign of male puberty is testicular enlargement.
This is important because families often look for more obvious changes such as:
- A deeper voice
- Penile growth
- Pubic or underarm hair
- Facial hair
- Acne
- A sudden growth spurt
Those generally aren't the best markers of whether central puberty has actually begun.
Some boys referred for “no puberty” have already developed subtle testicular enlargement that wasn't apparent to the family. Conversely, body odor and pubic hair can occur because of adrenarche, which involves adrenal hormones and can occur without true central puberty.
A physical examination therefore provides information that simply asking “Does he look like he's in puberty?” cannot.
For more, read What a Testicular Volume of 4 mL Means for Boys and Puberty.
What Are the Signs of Delayed Puberty in Boys?
The cardinal sign is no testicular enlargement by age 14, but delayed puberty can show up in several ways.
Parents may notice that their son has little or no genital development, has not experienced the expected acceleration in height, looks considerably less physically mature than his peers, or started showing signs of puberty but then seems to have stopped progressing.
Growth can provide another important clue.
In constitutional growth delay, boys are often short compared with peers of the same chronological age, but their height may make much more sense when compared with their delayed skeletal or bone age.
This is why height alone isn't enough.
A pediatric endocrinologist wants to know:
Is puberty late? Is growth late? Or are both late in a way that fits together?
Is My Son Just a Late Bloomer?
He may be.
Constitutional delay of growth and puberty (CDGP)—sometimes called self-limited delayed puberty—is by far the most common explanation for delayed puberty in boys.
Published estimates suggest it accounts for approximately 60–80% of boys presenting with delayed puberty.
These boys are otherwise healthy, but their biological clock is shifted later. Their bone age is often delayed, their growth pattern may look younger than their chronological age, and puberty eventually begins and progresses spontaneously.
Family history can be one of the strongest clues.
Approximately 50–75% of boys with constitutional delay have a parent or sibling who also matured later.
Dad may remember being one of the shortest boys in middle school and then growing dramatically in high school. A parent may remember entering puberty later than friends. An older sibling may have followed the same pattern.
Those stories matter.
But they don't prove the diagnosis.
Don't Let “He's a Late Bloomer” Become a Substitute for an Evaluation
This is where families can lose years.
A 13-year-old boy without obvious puberty may still fall within the normal range.
A 14-year-old boy whose testicles remain prepubertal meets the clinical definition of delayed puberty.
At that point, “let's wait another year” should not be the entire assessment.
The problem isn't that observation is always wrong. For a healthy boy with constitutional delay, observation may ultimately be exactly what is appropriate.
The problem is assuming constitutional delay before establishing that the growth and pubertal pattern actually fits it.
A family history of late puberty is reassuring. A delayed bone age can be reassuring. An otherwise healthy growth pattern can be reassuring.
But none of those should become an excuse to stop asking questions.
There is an important difference between:
“We evaluated him, his pattern is consistent with constitutional delay, and we're going to monitor his progression.”
and:
“He's probably a late bloomer. Let's just wait.”
Those are not the same thing.
What Causes Delayed Puberty in Boys?
There are three broad categories.
1. Constitutional Delay of Growth and Puberty
This is the most common cause.
The reproductive system is capable of functioning normally, but its activation occurs later than average. These boys frequently have delayed bone age and a family history of later maturation.
Puberty usually progresses spontaneously.
Constitutional delay is a variation of normal development—but that conclusion should come from understanding the child's pattern, not simply from the passage of time.
2. Hypogonadotropic Hypogonadism
In this group, the brain or pituitary gland is not providing enough of the hormonal signals—particularly LH and FSH—needed to stimulate the testicles.
This can be functional and potentially reversible, such as with:
- Undernutrition or inadequate energy availability
- Significant chronic illness
- Excessive exercise or intense training
- Certain medications
It can also be permanent or congenital.
One example is congenital hypogonadotropic hypogonadism (CHH). When this occurs with a reduced or absent sense of smell, it may be associated with Kallmann syndrome.
One of the challenges in pediatric endocrinology is that constitutional delay and congenital hypogonadotropic hypogonadism can initially look remarkably similar. Both may produce low, prepubertal levels of LH, FSH and testosterone.
There is no single routine blood test that perfectly separates the two.
3. Hypergonadotropic Hypogonadism
Here, the brain is sending the hormonal signals, but the testicles cannot respond normally.
LH and FSH therefore become elevated.
Potential causes include primary testicular dysfunction, certain chromosomal conditions such as Klinefelter syndrome (47,XXY), prior testicular injury, or effects from some forms of chemotherapy or radiation.
Understanding which category a boy falls into dramatically changes what happens next.
Can Growth Help Distinguish a Late Bloomer From a Medical Problem?
Yes—and this is one reason LIFE evaluates growth and puberty together.
A boy with constitutional delay often looks younger biologically than his chronological age.
His height may be below average for a 14-year-old, for example, while being much more appropriate for a child with his skeletal maturity.
That distinction can become visible on a bone age X-ray.
Growth velocity also matters.
A child who has consistently followed a lower growth percentile with delayed skeletal maturation tells a different story from a child whose height velocity has slowed unexpectedly or who has begun falling across percentiles.
The question isn't simply:
“How tall is he?”
It is:
“How has he been growing, where is he in puberty, and do those two stories agree?”
What Is Bone Age—and Why Does It Matter in Delayed Puberty?
A bone age is an X-ray, typically of the left hand and wrist, used to estimate skeletal maturity.
In constitutional growth delay, bone age is often younger than chronological age.
For example, a 14-year-old boy may have skeletal maturation more consistent with a younger adolescent. That can help explain why he is shorter than classmates and why his major pubertal growth spurt has not yet occurred.
But a delayed bone age is a clue, not a diagnosis.
It must be interpreted alongside growth velocity, pubertal development, family history and other clinical findings.
Read more in LIFE's guide to Tanner staging and bone age and our discussion of delayed bone age in boys.
How Is Delayed Puberty in Boys Evaluated?
A delayed-puberty evaluation starts with the child's story, growth pattern and physical development—not a long list of laboratory tests.
A pediatric endocrinologist reviews several years of height measurements and calculates growth velocity. Family history matters, including whether parents or siblings experienced later puberty or late growth spurts.
The history may also look for chronic illness, nutrition and energy availability, intense athletic training, medications, previous undescended testes, testicular injury, chemotherapy or radiation, and a reduced or absent sense of smell.
A clinical examination helps determine whether puberty has actually begun and how far it has progressed.
From there, testing is selected to answer specific questions.
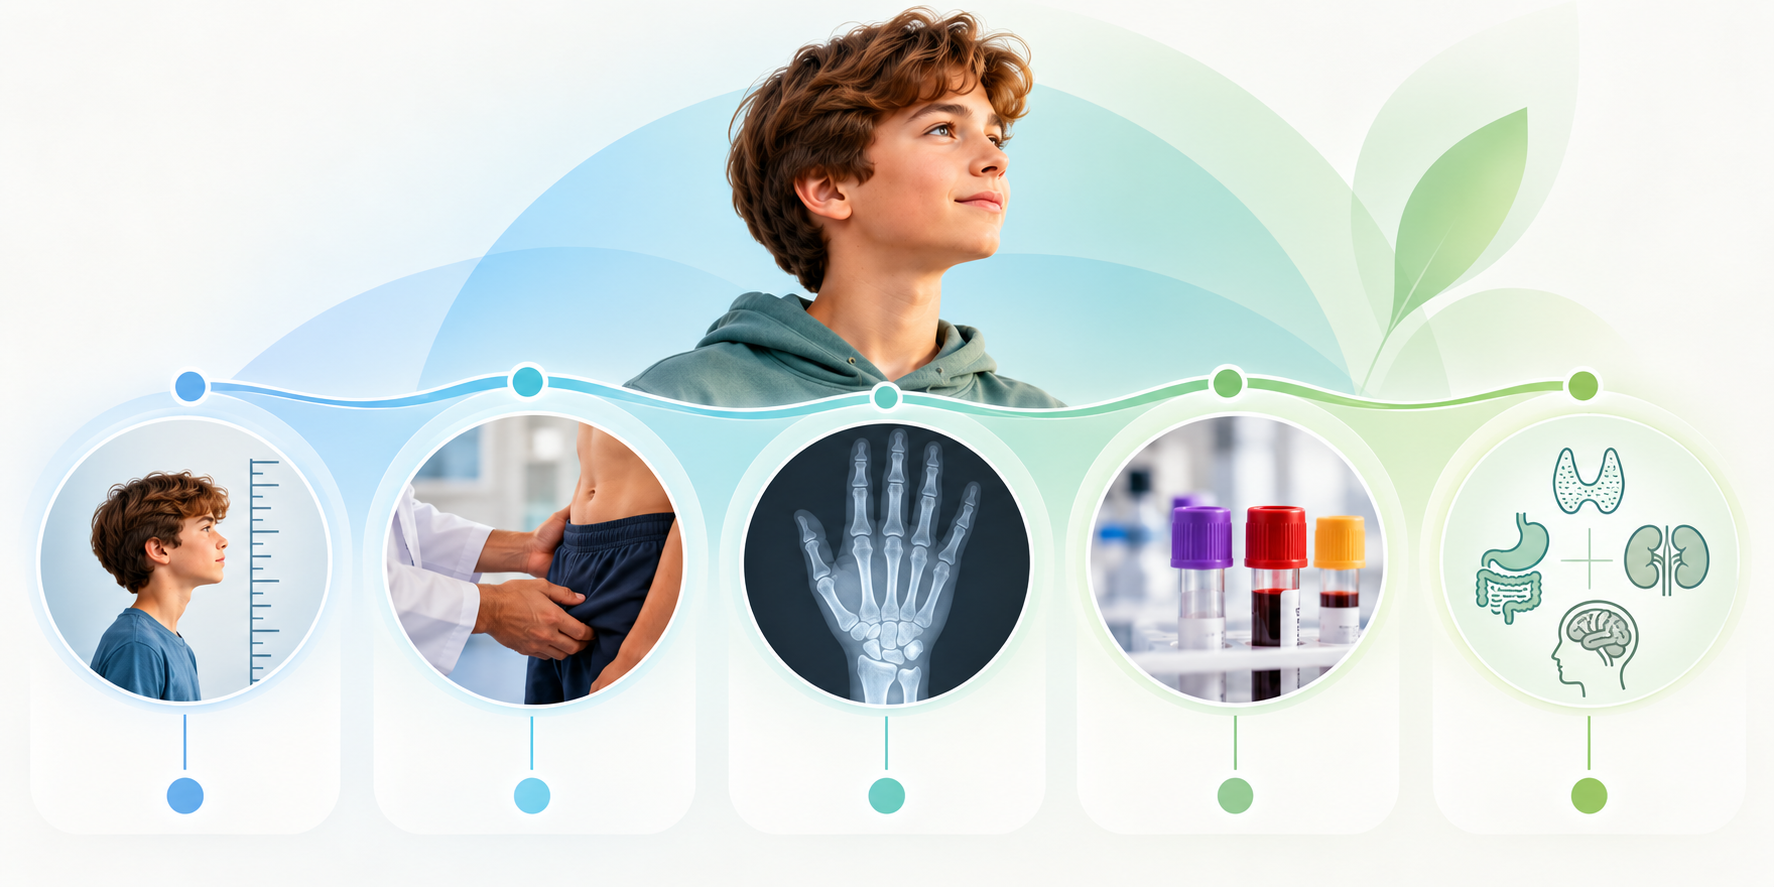 How delayed puberty in boys is evaluated: A pediatric endocrine evaluation looks at the complete pattern—not just age. Growth history and pubertal development are assessed first, followed when appropriate by a bone age X-ray, early-morning hormone testing and targeted testing for other medical or hormonal causes.
A bone age X-ray can provide information about skeletal maturity.
What Tests Are Used for Delayed Puberty in Boys?
Testing should answer a clinical question. Not every boy needs every laboratory test.
An initial pediatric endocrine evaluation may include an early-morning testosterone, LH and FSH, ideally obtained when these hormones can be interpreted appropriately for age and pubertal stage.
Depending on the history and growth pattern, additional testing may include:
- Thyroid function
- CBC
- Inflammatory markers such as ESR
- Kidney and liver function
- Electrolytes
- Celiac screening
- IGF-1
- Prolactin
The goal is not simply to “check hormones.” It is to determine whether puberty is delayed because of a normal developmental pattern, an issue affecting hypothalamic or pituitary signaling, primary testicular dysfunction, or another health condition suppressing normal development.
Why Are LH, FSH and Testosterone Important?
These three hormones help show where the pubertal signaling pathway may be interrupted.
The brain and pituitary stimulate puberty through LH and FSH. These hormones act on the testicles, which increase testosterone production as puberty progresses.
If testosterone is low and LH and FSH are elevated, the pattern may suggest that the pituitary is signaling appropriately but the testicles are not responding as expected.
If testosterone is low and LH and FSH are also low or prepubertal, the interpretation is more complicated.
That pattern can occur in both constitutional delay and hypogonadotropic hypogonadism.
This is one of the reasons a single hormone panel should never be interpreted in isolation.
Numbers need context.
Can a Blood Test Prove That My Son Is Just a Late Bloomer?
Not always.
This is one of the most important nuances in delayed puberty.
There is currently no single basal or stimulation test that reliably distinguishes constitutional delay of growth and puberty from congenital hypogonadotropic hypogonadism in every boy.
Additional markers such as inhibin B and AMH may sometimes contribute useful information. More specialized testing—including pituitary evaluation, imaging, smell testing or genetic testing—may be appropriate when the clinical picture raises concern.
But sometimes the answer becomes clear only through careful longitudinal observation of growth and pubertal progression.
That is very different from passive waiting.
Observation is useful when you know what you're measuring and what should happen next.
When Is an MRI Needed for Delayed Puberty?
Most boys with delayed puberty do not automatically need an MRI.
Imaging may be considered when the history, examination or laboratory pattern raises concern for a hypothalamic or pituitary cause.
That might include abnormalities involving other pituitary hormones, neurological symptoms or other clinical findings suggesting a central disorder.
Testing should be targeted to the child—not ordered simply because puberty is late.
When Might Genetic Testing Be Considered?
Genetic testing may be appropriate when the clinical or laboratory pattern suggests an inherited or chromosomal cause.
For example, elevated gonadotropins may prompt chromosome analysis when conditions such as Klinefelter syndrome are being considered.
A pattern suggesting congenital hypogonadotropic hypogonadism may lead to more specialized genetic evaluation.
Again, not every late bloomer needs genetic testing.
The evaluation becomes progressively more specific based on what the initial history, examination, growth pattern, bone age and laboratory results show.
Does Delayed Puberty Affect Adult Height?
This question is more nuanced than “late bloomers eventually catch up.”
Many boys with constitutional delay experience substantial catch-up growth as puberty progresses.
But delayed puberty has traditionally been treated as entirely benign, and emerging evidence suggests that self-limited delayed puberty may have implications for adult height, bone health and psychosocial well-being in at least some individuals.
That doesn't mean every boy with delayed puberty needs treatment.
It means delayed puberty deserves thoughtful evaluation rather than dismissal.
Bone age can also help estimate how much growth may remain by showing how far the skeleton has progressed toward maturity.
Can Delayed Puberty Affect Confidence and Mental Health?
Absolutely.
For an adolescent boy, being years behind friends physically can feel much bigger than a percentile on a growth chart.
He may be shorter, have less muscle development, look younger, have a higher voice and feel visibly different in a locker room or athletic setting.
Some boys are not bothered by it.
Others are deeply bothered and simply don't say so.
Psychosocial impact is therefore part of the medical conversation—not an afterthought.
The goal isn't to make every child develop on the same timeline. It is to understand whether the timeline is healthy and recognize when delayed development is meaningfully affecting the child.
Does Delayed Puberty Need Treatment?
Not always.
A healthy boy with constitutional delay may simply need monitoring and reassurance once the pattern has been appropriately evaluated.
In other situations, a pediatric endocrinologist may discuss a short course of sex-steroid therapy, depending on the child's age, pubertal status, underlying diagnosis and psychosocial circumstances.
For boys with permanent hypogonadism, treatment is different and may require longer-term hormone replacement.
The important point is that treatment follows the diagnosis.
The first goal isn't to make puberty happen faster. It's to understand why it hasn't happened yet.
What If My Son Is 13 and Hasn't Started Puberty?
At 13, he may still be within the normal range.
Male puberty normally begins across a fairly broad window, approximately ages 9 to 14.
But the birthday alone should not decide whether questions deserve attention.
If a 13-year-old is also growing unusually slowly, falling across height percentiles, substantially shorter than expected for his family, has a history of chronic illness or has other concerning symptoms, evaluation may be reasonable before age 14.
You do not have to wait for a child to cross a diagnostic cutoff before asking whether his growth pattern makes sense.
What If My Son Is 14 and Hasn't Started Puberty?
If a boy has no testicular enlargement by age 14, he meets the standard definition of delayed puberty and should be evaluated.
This does not mean something is necessarily wrong.
It means there is now enough delay that determining why is appropriate.
For many boys, the answer will be reassuring.
But reassurance is far more valuable when it comes from understanding the pattern than when it comes from another year of guessing.
What If My Son Is 15 or 16 and Still Looks Prepubertal?
At 15 or 16, continued absence of meaningful pubertal development deserves pediatric endocrine evaluation if it has not already occurred.
The older a boy becomes without progression, the less useful it is to rely solely on “he'll get there eventually.”
The evaluation is not just about identifying disease.
It can help determine:
- Whether puberty has actually begun
- Whether development is progressing
- Whether growth and skeletal maturity fit constitutional delay
- Whether laboratory testing suggests another cause
- How much growth may remain
- Whether treatment should even be part of the conversation
For families who have been told to wait repeatedly, that information can replace uncertainty with an actual plan.
When Should Parents See a Pediatric Endocrinologist?
Consider a pediatric endocrine evaluation when a boy:
- Has no testicular enlargement by age 14
- Started puberty but appears to have stopped progressing
- Is growing unusually slowly
- Is dropping across height percentiles
- Is substantially shorter than expected for his family
- Has a markedly delayed bone age that has not been explained
- Has symptoms suggesting chronic illness or another hormonal condition
- Has a history of chemotherapy, radiation, testicular injury or undescended testes
- Has little or no sense of smell along with absent puberty
- Is significantly distressed by delayed physical development
An evaluation does not commit a family to treatment.
It provides something much more fundamental first:
an explanation.
“Wait and See” Should Come After Understanding the Pattern
Many boys with delayed puberty really are healthy late bloomers.
That is good news.
But it is also why delayed puberty can be easy to dismiss.
A common diagnosis should not become an assumed diagnosis.
There is nothing inherently wrong with waiting when the history, examination, growth pattern, bone age and appropriate testing support constitutional delay.
There is a meaningful difference between watchful monitoring and passive waiting.
Watchful monitoring means we understand the likely pattern, know what changes we expect to see, know when we expect to see them, and know what would cause us to look deeper.
Passive waiting means hoping.
Families deserve better than hope alone.
Frequently Asked Questions About Delayed Puberty in Boys
What age is puberty considered delayed in boys?
Puberty is considered delayed when there is no testicular enlargement by age 14.
What is the most common cause of delayed puberty in boys?
The most common cause is constitutional delay of growth and puberty, also called self-limited delayed puberty. Published estimates suggest it accounts for roughly 60–80% of boys presenting with delayed puberty.
How can I tell if my son is a late bloomer?
Family history, growth pattern, pubertal examination and bone age can all provide clues, but there is no single home sign or blood test that proves a boy is simply a late bloomer.
Does delayed bone age mean my son is a late bloomer?
Not necessarily. Delayed bone age is common in constitutional growth delay, but it must be interpreted with the child's growth velocity, pubertal stage, family history and other findings.
What blood tests are checked for delayed puberty?
Initial testing commonly includes early-morning LH, FSH and testosterone. Depending on the child's history and growth pattern, thyroid studies, CBC, inflammatory markers, celiac screening, metabolic testing, IGF-1, prolactin or other tests may be appropriate.
Can delayed puberty run in families?
Yes. Constitutional delay has a strong familial component, and approximately 50–75% of affected boys have a parent or sibling with a history of later pubertal development.
Will a late bloomer eventually go through puberty?
Most boys with constitutional delay eventually begin and progress through puberty spontaneously. The important step is determining whether the child's pattern is actually consistent with constitutional delay.
Should I wait until my son is 14 before seeing an endocrinologist?
Not necessarily. Age 14 is the standard threshold for delayed puberty in boys, but earlier evaluation can be appropriate when growth is unusually slow, height percentiles are falling, there are other symptoms or the growth pattern does not make sense.
Understand Why Puberty Is Delayed
If your son is approaching or past age 14 without clear pubertal development—or if his growth and puberty simply do not seem to fit together—an individualized pediatric endocrine evaluation can provide clarity.
The goal is not to turn every late bloomer into a patient who needs treatment.
It is to determine which boys are healthy late bloomers and which boys need something more than time.
LIFE Pediatric Endocrinology evaluates growth, skeletal maturity and puberty together so families understand where their child is now, what may happen next and whether intervention should even be considered.
Contact LIFE Pediatric Endocrinology →
About Dr. Payal Patel
Payal Patel, MD, is a board-certified pediatric endocrinologist at LIFE Pediatric Endocrinology, where growth and puberty are a flagship focus of her practice. She joined LIFE after practicing with Phoenix Children's and Banner Health in Arizona and has particular experience guiding children through growth and puberty after cancer treatment.
Her approach pairs evidence-based pediatric endocrinology with close attention to nutrition, sleep, lifestyle and each family's individual goals.
Read Dr. Payal Patel's full bio →
References
- Argente J, Dunkel L, Kaiser UB, et al. Molecular Basis of Normal and Pathological Puberty: From Basic Mechanisms to Clinical Implications. The Lancet Diabetes & Endocrinology. 2023;11(3):203–216. doi:10.1016/S2213-8587(22)00339-4. PubMed
- Koysombat K, Tsoutsouki J, Patel AH, et al. Kisspeptin and Neurokinin B: Roles in Reproductive Health. Physiological Reviews. 2025;105(2):707–764. doi:10.1152/physrev.00015.2024. PubMed
- Saengkaew T, Howard SR. Genetics of Pubertal Delay. Clinical Endocrinology. 2022;97(4):473–482. doi:10.1111/cen.14606. PubMed
- Abreu AP, Kaiser UB. Pubertal Development and Regulation. The Lancet Diabetes & Endocrinology. 2016;4(3):254–264. doi:10.1016/S2213-8587(15)00418-0. PubMed Central (PMC)
- Bakhtiani P, Geffner M. Delayed Puberty. Pediatrics in Review. 2022;43(8):426–435. doi:10.1542/pir.2020-005291. American Academy of Pediatrics
- Salonia A, Rastrelli G, Hackett G, et al. Paediatric and Adult-Onset Male Hypogonadism. Nature Reviews Disease Primers. 2019;5:38. doi:10.1038/s41572-019-0087-y. Nature
- Zhu J, Chan YM. Adult Consequences of Self-Limited Delayed Puberty. Pediatrics. 2017;139(6):e20163177. doi:10.1542/peds.2016-3177. PubMed Central (PMC)
- Howard SR. Interpretation of Reproductive Hormones Before, During and After the Pubertal Transition—Identifying Health and Disordered Puberty. Clinical Endocrinology. 2021;95(5):702–715. doi:10.1111/cen.14578. Wiley Online Library
- Ahmed SF, Achermann J, Alderson J, et al. Society for Endocrinology UK Guidance on the Initial Evaluation of a Suspected Difference or Disorder of Sex Development (Revised 2021). Clinical Endocrinology. 2021;95(6):818–840. doi:10.1111/cen.14528. PubMed
- Wei C, Davis N, Honour J, Crowne E. The Investigation of Children and Adolescents With Abnormalities of Pubertal Timing. Annals of Clinical Biochemistry. 2017;54(1):20–32. doi:10.1177/0004563216668378. Sage Journals
- Persani L, Bonomi M, Cools M, et al. ENDO-ERN Expert Opinion on the Differential Diagnosis of Pubertal Delay. Endocrine. 2021;71(3):681–688. doi:10.1007/s12020-021-02626-z.
Medical Disclaimer
This article is for educational purposes only and does not replace individualized medical advice, diagnosis or treatment. Growth and pubertal development vary from child to child. Families with concerns about a child's growth or puberty should seek individualized guidance from a qualified healthcare professional.